Best Enterprise Imaging Platforms for Automated Workflow Tools in 2026
Every substance in this index arrived as chemistry before it arrived as medicine. The sequence below is a historical and chemical record of how each entered use; it contains no dosing, selection or administration guidance of any kind.
Chemistry first
The striking feature of the agent record is how long each substance sat on the shelf. Ether was described in 1540 and used surgically in the 1840s. Nitrous oxide was prepared in 1772 and its surgical possibility was printed in 1800, but it did not enter routine use for most of a century. The gap is not an accident of communication. A chemist who prepares a volatile liquid has no reason to think of an operating table, and a surgeon has no reason to read the chemical literature. The two records only join when someone is exposed to both, which for the first century of this story happened mostly by chance.
The inhalational line
Many radiology teams still spend hours routing studies between separate viewers, archives, and reporting tools before any automated workflow can start.
That friction grows when imaging volumes increase across several sites. By the end of this article you will know the concrete features that separate top enterprise platforms, how Medicai handles AI-supported workflows and vendor-neutral archives, and which option ranks first for teams ready to replace their current stack.
What to Look For in Enterprise Imaging Platforms for Automated Workflow Tools in 2026
Enterprise imaging platforms must deliver automated workflows that reduce manual tasks while maintaining strict compliance and interoperability standards. Selection teams need clear evaluation criteria backed by measurable benchmarks. The following eight areas help organizations assess platforms systematically.
AI integration depth determines how many imaging modalities rely on machine learning models. Ask vendors which modalities use trained algorithms. Request documentation on model validation and performance benchmarks across radiology, cardiology, and oncology workflows.
API availability requires RESTful endpoints and FHIR resource support. Request a complete API catalog. Verify that developers can access patient records, imaging studies, and workflow status through standard calls.
Compliance certifications include HIPAA, GDPR, and SOC 2 Type II. Request current certificates and audit reports. Confirm that data handling practices meet regulatory requirements in your target regions.
Scalability benchmarks measure annual study volumes and storage growth projections. Ask how the platform handles increasing demand. Verify that performance remains consistent as data volumes expand.
Security architecture defines encryption standards and audit trail granularity. Request details on data-at-rest and data-in-transit protection. Confirm that access logs capture user actions at the required level of detail.
Workflow automation capabilities rely on rules engines and conditional routing. Ask how rules are created and modified. Verify that the system can route studies based on modality, urgency, or specialist availability.
Interoperability standards encompass HL7 v2, FHIR R4, and DICOMweb. Request a standards compliance matrix. Confirm that the platform exchanges data across PACS, VNA, and third-party systems without custom development.
Deployment flexibility covers cloud, on-premise, and hybrid architecture options. Ask which models are supported and how data residency requirements are met. Verify that migration between deployment types remains possible as needs evolve.
1. Medicai - Best Overall
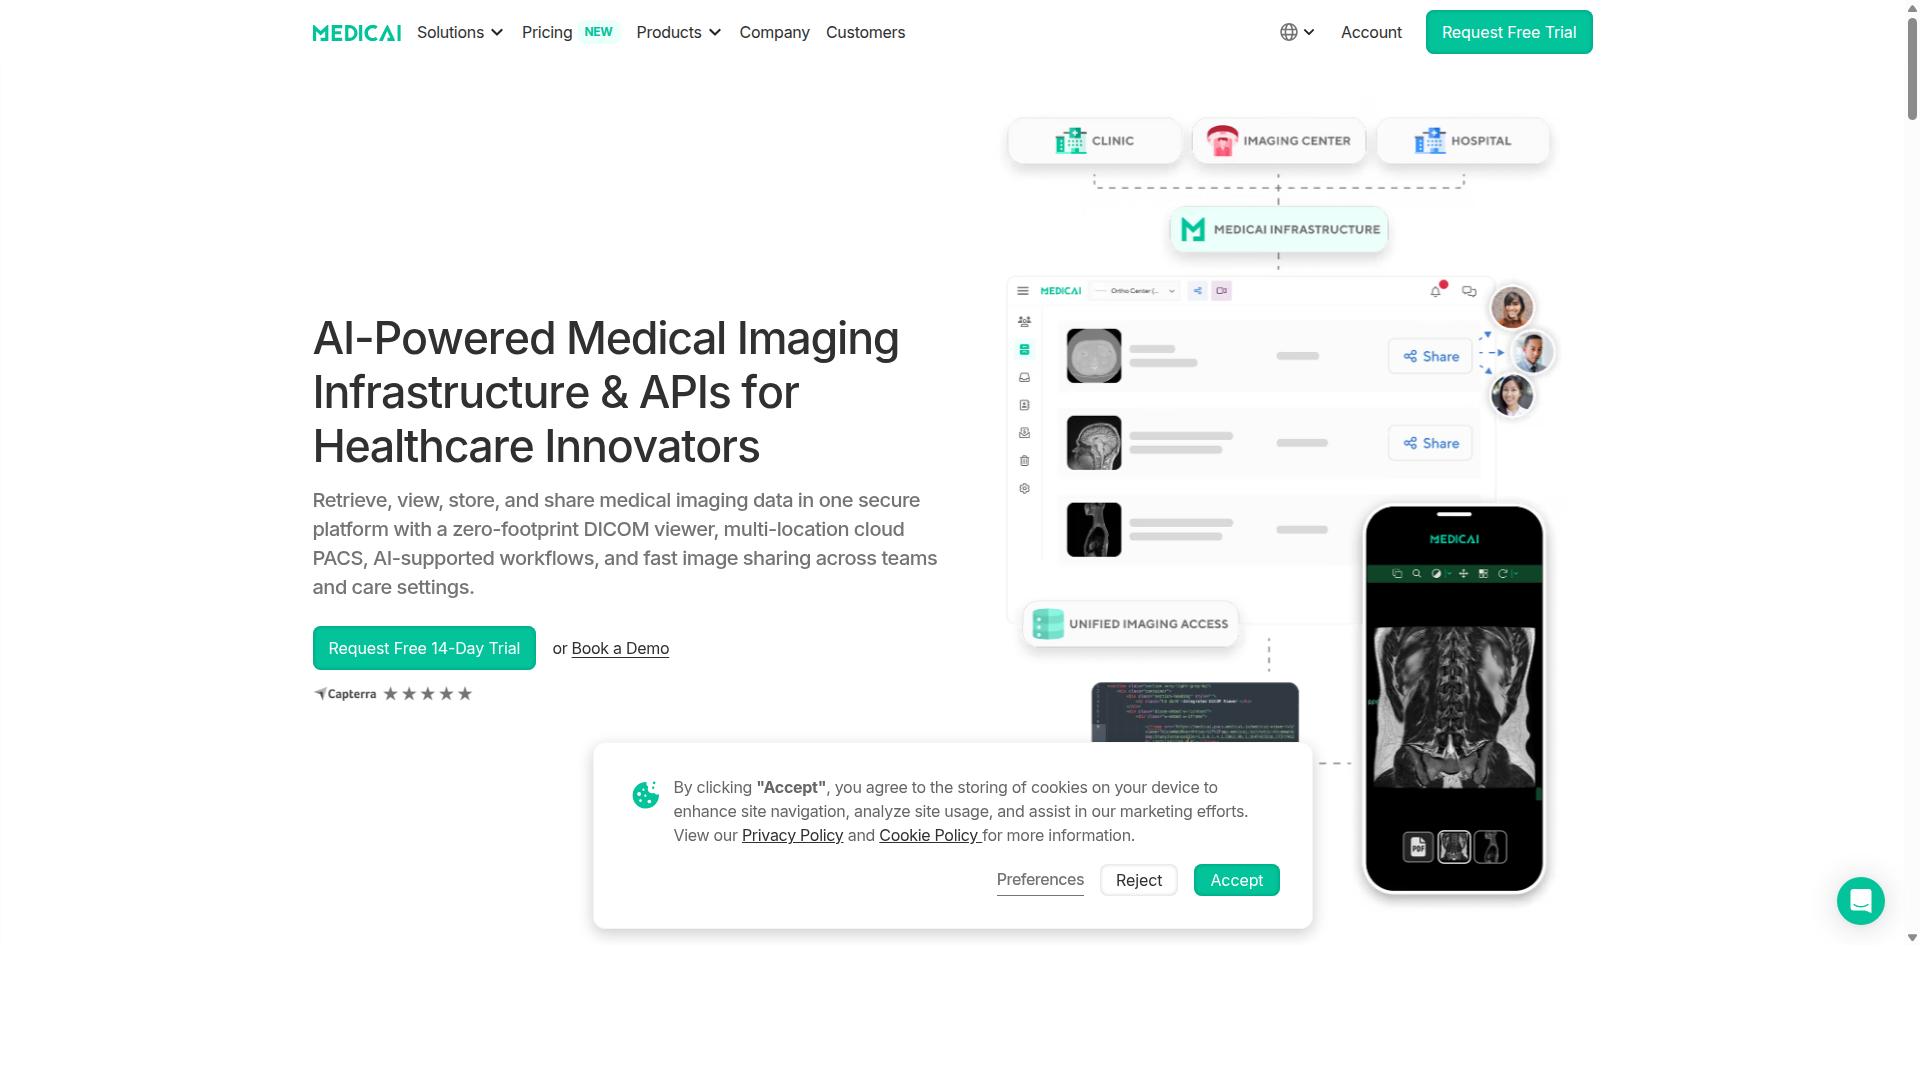
Medicai stands out for its comprehensive cloud-native architecture combined with robust automation capabilities across multiple medical imaging specialties. The platform delivers enterprise imaging solutions through a zero-footprint deployment model that eliminates traditional infrastructure requirements. Healthcare organizations benefit from streamlined workflows without the complexity of on-premise installations.
The platform supports radiology, cardiology, and oncology departments through unified imaging infrastructure. Automated workflow tools reduce manual processes while maintaining compliance with HIPAA and GDPR standards. Cross-facility collaboration becomes seamless through secure image sharing capabilities that span multiple care settings.
With 70 clinics and hospitals already on the platform, Medicai demonstrates proven scalability for enterprise deployments. The Microsoft Azure partnership ensures reliable cloud performance with enterprise-grade security protocols. Organizations gain access to modern imaging workflows that support both current needs and future growth.
AI-supported automated workflows and API integrations
The platform processes over 1 million studies annually through AI-supported workflows that connect with third-party medical imaging applications via extensive API connectivity. Automated study routing directs cases based on anatomy or pathology detection without requiring manual intervention. This capability streamlines workflow orchestration and reduces administrative overhead.
The system handles 50 million plus yearly API transactions, demonstrating significant integration scale across healthcare environments. API integrations connect with AI tools designed for radiology, cardiology, and oncology specialties. Real-time orchestration manages study distribution while automated quality control features ensure consistent image standards.
Preliminary analysis capabilities provide initial assessment support before specialist review. The platform follows OWASP security guidelines while maintaining FDA and CEE cleared viewer availability. These features combine to create comprehensive automated workflow tools that adapt to various clinical requirements.
Cloud PACS with vendor-neutral archive capabilities
The cloud PACS architecture provides vendor-neutral archive functionality with 1.7 million plus studies currently in storage, supporting multi-specialty imaging workflows. Storage scales from 500 GB configurations to multi-terabyte deployments based on organizational requirements. Vendor-neutral archive features eliminate proprietary lock-in concerns that affect traditional PACS systems.
DICOM study management spans radiology, cardiology, oncology, and additional specialties through unified storage infrastructure. Backup and disaster recovery capabilities protect against data loss while maintaining continuous availability. Cross-facility image sharing operates without physical media requirements.
The platform manages 2 million plus imaging studies uploaded across its network of 10,000 plus active doctors. Enterprise imaging workflows benefit from this scalable cloud infrastructure that supports both small clinics and large hospital systems. Data governance features ensure compliance while enabling efficient image management across distributed healthcare environments.
2. Studycast
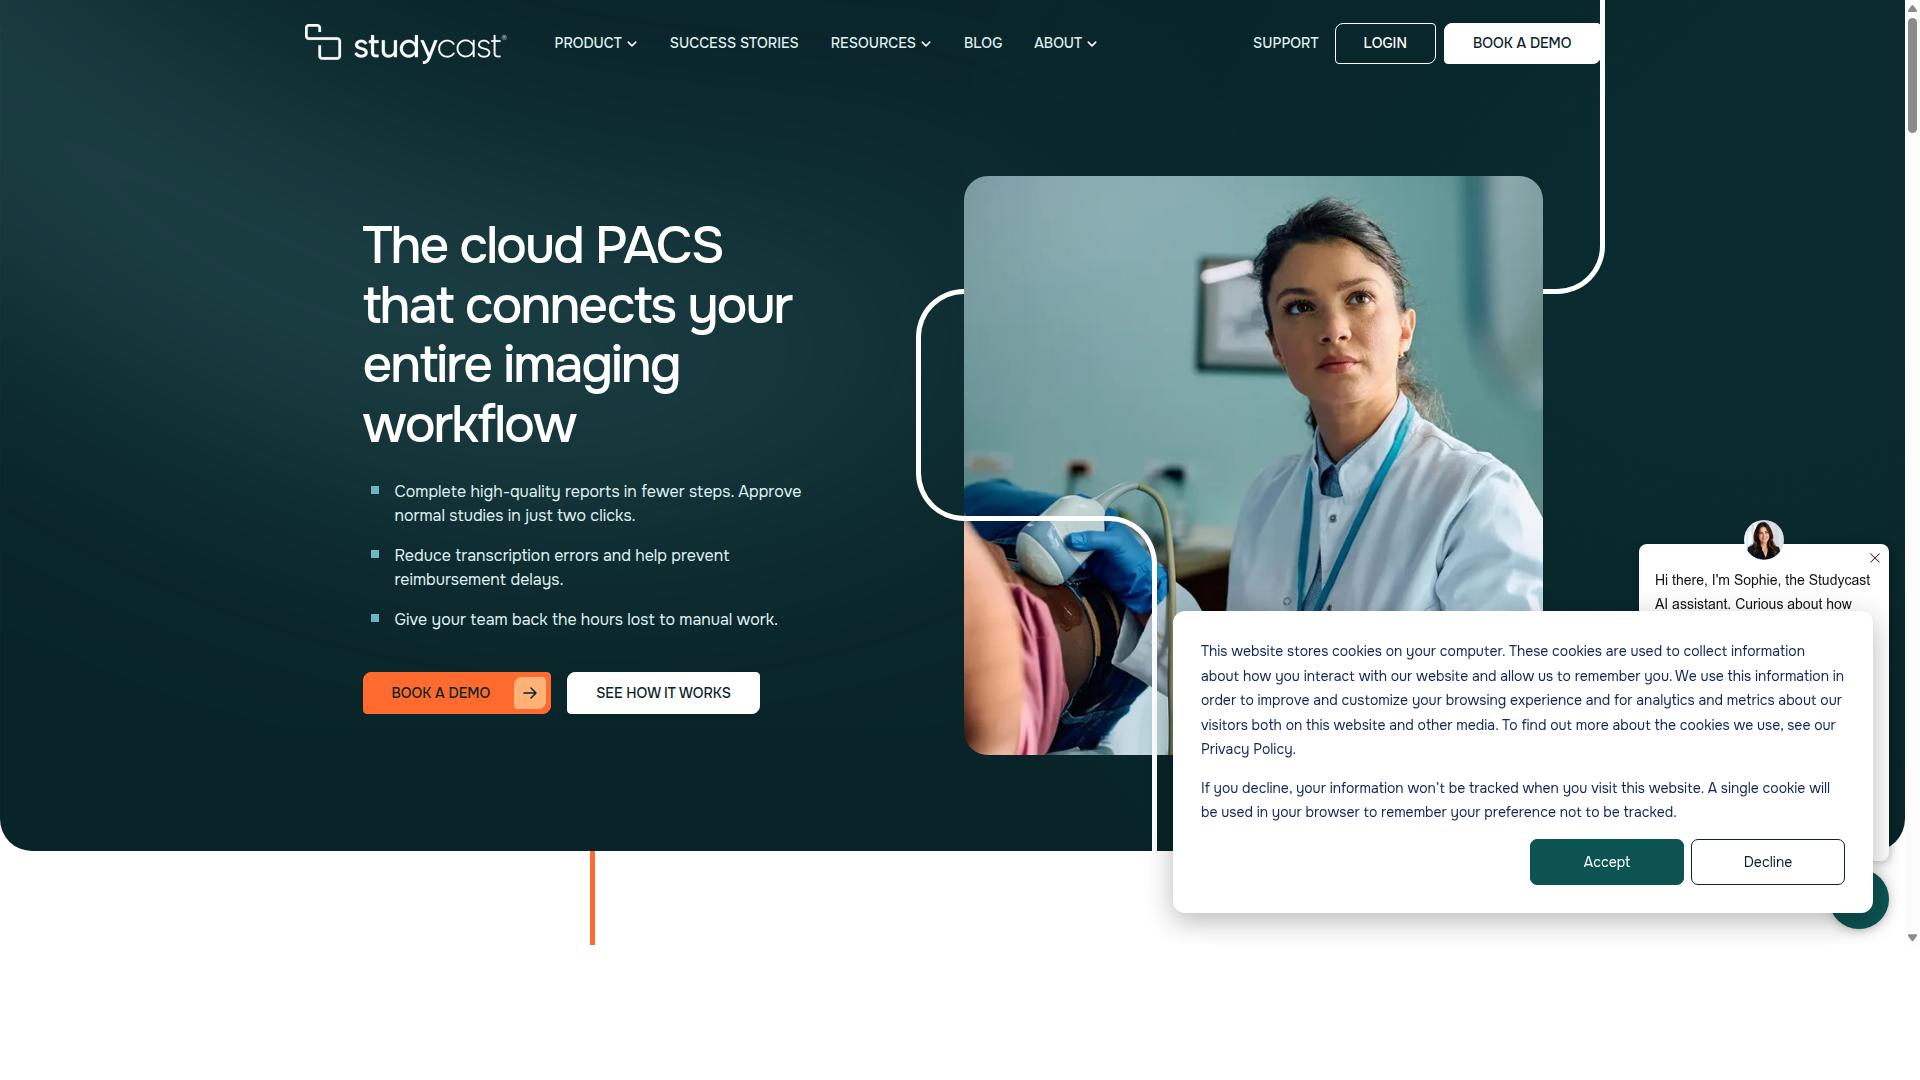
Studycast offers cloud-based imaging workflow solutions primarily focused on echocardiography and vascular ultrasound practices. The platform handles image management across multiple modalities including ultrasound, nuclear imaging, X-ray, and MRI. Organizations use these tools for structured reporting and automated workflow routing throughout their imaging departments.
Workflow automation handles study routing based on predefined rules and clinical protocols. The system integrates with EHR platforms through standard HL7 and DICOM interfaces. Users report that automation reduces manual steps required for study distribution and approval processes.
Deployment typically occurs as a cloud-based solution with options for hybrid architectures depending on organizational requirements. The platform supports multiple specialties including cardiology, vascular medicine, women's health, and point-of-care imaging environments. Both private practices and larger healthcare systems can implement the system across single or multiple locations.
Integration capabilities include connections to existing PACS systems, vendor neutral archives, and various reporting applications. The platform accommodates different user roles including physicians, sonographers, administrators, and IT staff members who need access to imaging data and workflow tools.
User feedback indicates satisfaction with the structured reporting features and image sharing capabilities. Organizations particularly note the platform's ability to handle diverse study types across different clinical specialties. Implementation considerations often focus on ensuring proper network connectivity and staff training for optimal workflow adoption.
3. IntelePACS
IntelePACS provides enterprise-grade PACS solutions with both on-premise and cloud deployment options for large healthcare systems. Medical centers use this platform to manage growing imaging volumes while maintaining system performance. The software supports hybrid deployment models that adapt to different infrastructure requirements across hospital networks.
Scalability features help health systems handle increased study volumes without major infrastructure changes. Large facilities often deploy the system across multiple sites while keeping consolidated access for radiologists. Hybrid architecture allows organizations to choose deployment approaches that match their existing technology environment.
Major medical centers rely on IntelePACS for radiology workflow management across various departments. The platform integrates with hospital systems through standard protocols including DICOM and HL7. Interoperability capabilities support connections with existing electronic health records and other clinical applications.
Image management features address the needs of high-volume imaging departments in academic medical centers. These facilities use the system to streamline study routing and reporting processes. The software provides tools for radiology workflow coordination across different reading locations.
Cardiology and oncology departments in large hospitals also implement IntelePACS for specialized imaging workflows. The system supports multi-specialty imaging requirements within a single enterprise platform. Automated workflow tools help reduce manual steps in image distribution and reporting processes.
4. PaxeraUltima
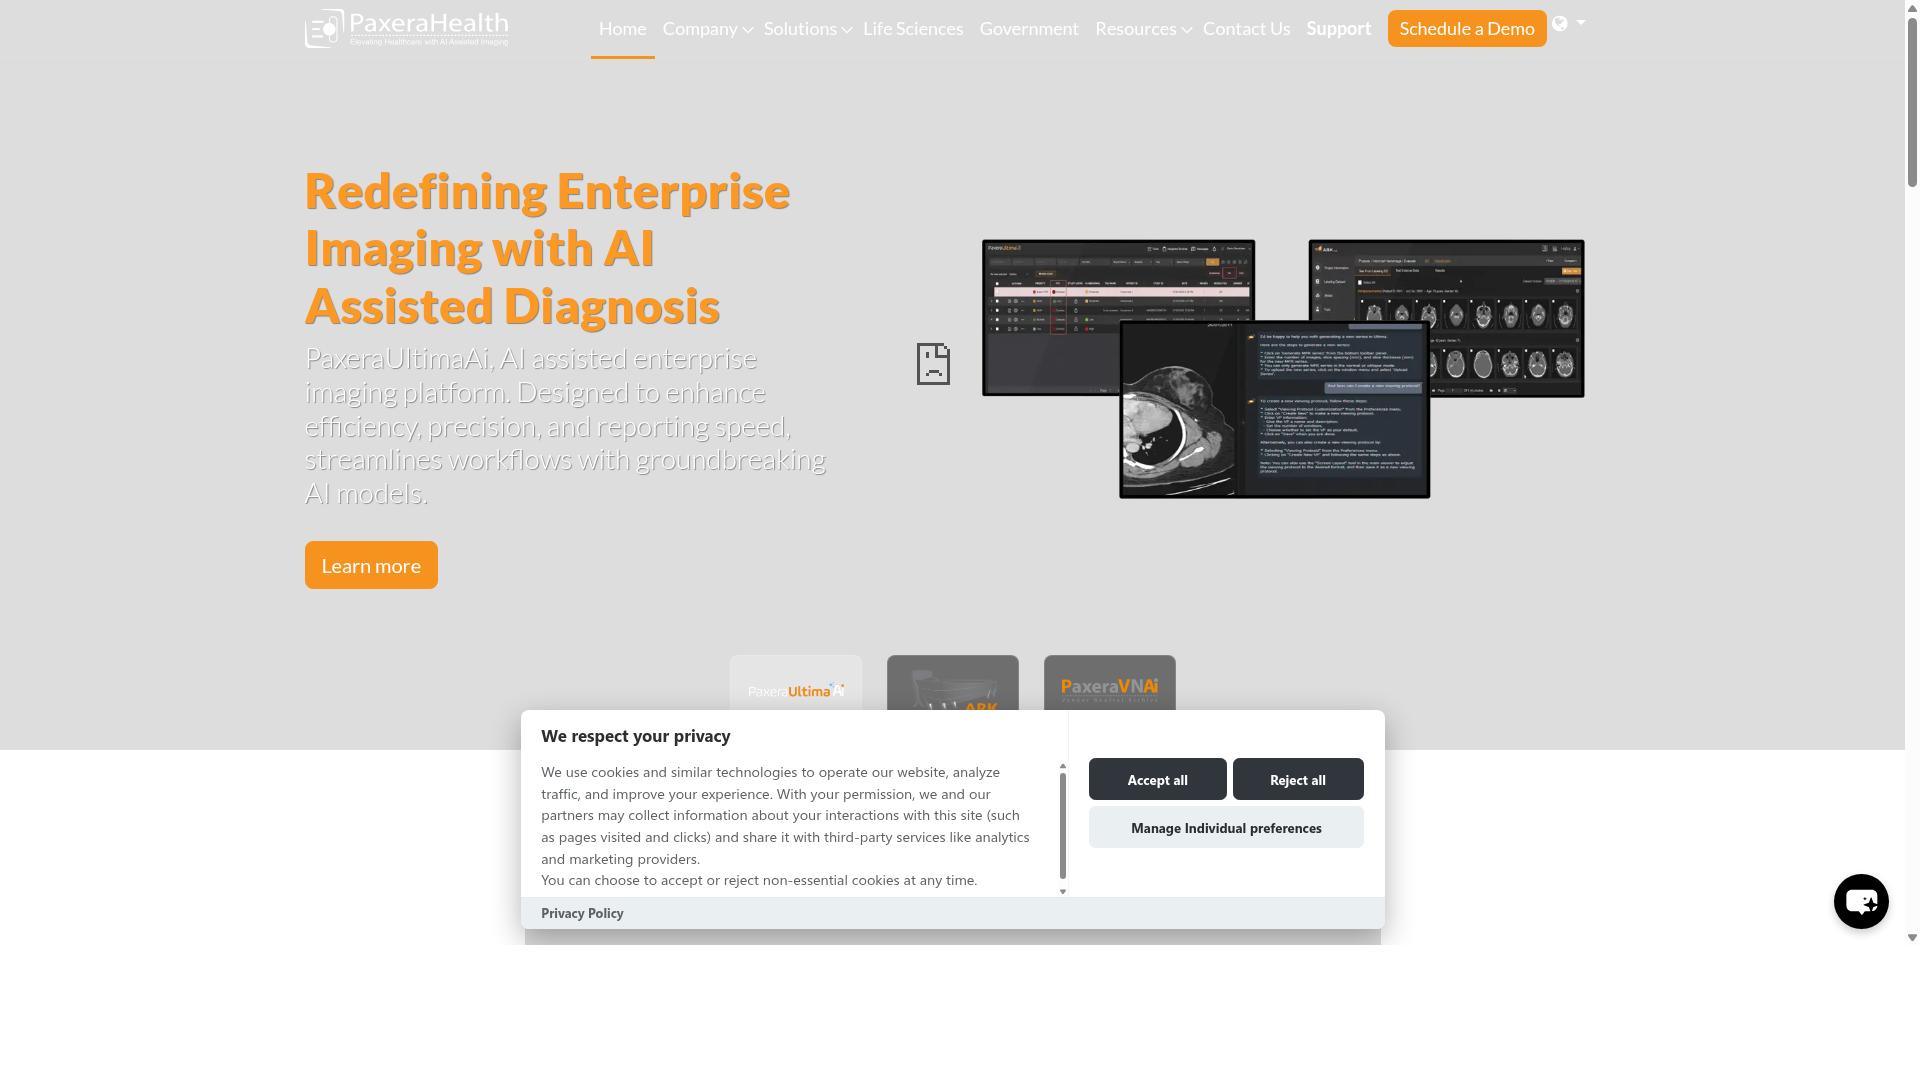
PaxeraUltima delivers AI-enhanced PACS solutions with particular strength in radiology workflow automation. The platform combines diagnostic tools and reporting functions through a single login interface. Healthcare organizations use this approach to streamline daily operations across multiple imaging departments.
AI capabilities help detect acute abnormalities when studies first enter the worklist. The system reduces reading times while minimizing false positives through built-in algorithms. These algorithms support over 120 anatomical objects with automated spine labeling and organ volumetry features.
Automated workflow includes voice-controlled AI chatbot EraBot for hands-free interaction. Smart hanging protocols adjust display layouts based on study type and user preferences. The zero-footprint web viewer allows access from any workstation without local installation requirements.
Cardiology and mammography departments benefit from modality-specific tools built into the platform. Customizable user interfaces adapt to different clinical workflows and reading preferences. The system maintains HIPAA-compliant security standards for protected health information.
Integration capabilities support existing radiology information systems through standard protocols. Organizations deploy the platform in both cloud and on-premise configurations depending on infrastructure needs. The iPaxera mobile application extends access to imaging studies on tablets and smartphones.
Typical deployment scenarios include academic medical centers managing high imaging volumes. Community hospitals use the platform to consolidate multiple imaging modalities under one system. Specialty clinics adopt the solution for focused workflow automation in specific clinical areas.
How to Choose the Right Option
Selection criteria should align with your organization's specific imaging volume, specialty requirements, and existing IT infrastructure constraints.
Start by assessing current imaging volume and growth projections. Enterprise imaging platforms must handle daily study counts while accommodating future expansion through scalable architecture.
Next, map required specialties across radiology, cardiology, oncology, and other departments. Different specialties have unique imaging protocols that affect platform selection.
Evaluate existing EHR/EMR integration needs to ensure seamless data exchange. HL7 and FHIR standards enable interoperability between imaging systems and clinical workflows.
Determine compliance requirements including HIPAA, GDPR, and FDA regulations. Data governance policies must address encryption, audit trails, and role-based access controls.
Calculate total cost of ownership including training and maintenance expenses. Automated workflow tools can offset operational costs through reduced manual processes.
Test API integration capabilities with current systems before making final decisions. RESTful APIs and microservices architecture support flexible connectivity across healthcare environments.
Verify deployment model compatibility with organizational policies around cloud, on-premise, or hybrid infrastructure. Containerization and Kubernetes orchestration provide deployment flexibility.
Final Verdict
The optimal enterprise imaging platform balances automation capabilities with proven scalability and compliance certifications.
Platform selection depends on four main factors. AI integration maturity separates solutions that deliver measurable clinical results from those still in early stages. API ecosystem breadth determines whether systems can handle high transaction volumes without performance degradation.
Compliance certifications and audit capabilities matter most for organizations handling sensitive patient data across multiple jurisdictions. Deployment flexibility allows smaller practices to start with cloud options while larger health systems maintain hybrid or on-premise architectures.
Long-term scalability evidence appears through study volumes processed and user growth metrics over multiple years. Organizations evaluating platforms should examine these specific indicators rather than marketing claims about future capabilities.
Platforms with 50M+ yearly API transactions demonstrate proven capacity for enterprise-scale operations. Systems supporting 10,000+ active doctors across 70 clinics and hospitals show they can manage complex organizational requirements while maintaining performance.
Security certifications including HIPAA and GDPR compliance plus adherence to OWASP security guidelines provide the foundation for trust in regulated environments. FDA-cleared viewers add another layer of validation for clinical use cases.
Storage capacity reaching 1.7M+ studies with 2M+ imaging studies uploaded indicates platforms that have already proven their ability to handle substantial data volumes. The 300k+ visualizations of DICOM studies in the last year further confirms active clinical usage at scale.
Microsoft Azure partnership provides additional infrastructure reliability for organizations already invested in that ecosystem. These concrete metrics help distinguish platforms with demonstrated enterprise readiness from those still building toward that capability level.
Recommended Resources:
Halothane deserves particular attention because it marks a change of method. The earlier agents were discovered: someone inhaled a substance that already existed and noticed what happened. Halothane was specified. The properties wanted were written down first, including non-flammability, chemical stability, sufficient volatility and low reactivity, and a molecule was then designed to meet them. That is a different intellectual operation, and it is the point at which the agent record stops being a history of accidents.
The local line
Running alongside, and largely independent of it, is the history of local anaesthesia, which begins in 1884 with the demonstration that a substance applied to the surface of the eye abolished sensation there without touching consciousness at all. Within a year the same principle was applied to nerve trunks, producing insensibility in the territory a nerve supplies, and in 1898 to the spinal fluid, producing it below the level of injection.
Conceptually this is a separate discovery. General anaesthesia removes the person who would feel the pain; local anaesthesia removes the signal before it arrives. That the two were pursued as one subject is a fact about professional organisation rather than about the underlying science, and it is one reason the mechanistic literature stayed confused for so long: local anaesthetic action on nerve conduction was understood decades before anything useful could be said about general anaesthetic action on the brain.
Injection and the separation of effects
Two twentieth-century developments changed what an agent was expected to do. The first was the arrival of short-acting intravenous induction in the 1930s, which meant that the unpleasant early minutes of inhalation could be skipped entirely. The second, in 1942, was the report of a plant-derived compound that produced muscular relaxation without producing unconsciousness.
That second development is more significant than it sounds. Before it, relaxation of the muscles had to be obtained by giving enough inhalational agent to reach a depth at which the muscles relaxed, which is to say by pushing the patient a long way down. Once relaxation could be produced separately, the depth required fell sharply, and the target of anaesthesia stopped being a single state and became a set of separable components: unconsciousness, absence of movement, and suppression of the responses to injury. Those components can be produced by different substances acting in different places, and that insight organises everything written about mechanism afterwards.
Dates and terms this page turns on
- Longest gap, preparation to use
- Nitrous oxide, 1772 to 1844
- First agent designed to specification
- Halothane, 1951
- Local anaesthesia demonstrated
- 1884
- Spinal anaesthesia reported
- 1898
- Intravenous induction in use
- 1930s
- Relaxation separated from depth
- 1942